Arthrosamid Candidate Selection Follows Strict Clinical Criteria

✅ Medically reviewed | Updated september 2026
An arthrosamid candidate is typically an adult with mild-to-moderate knee osteoarthritis. Relief has usually not come from standard treatment already tried. Knee osteoarthritis affects around 8.75 million people across the UK. That number is rising steadily as the population ages. Many patients eventually consider injection-based options once tablets and physiotherapy stop working. Not every patient fits the profile Arthrosamid injection was designed for. The treatment is not currently funded on the NHS and is accessed privately. Clinics increasingly rely on structured screening rather than a quick judgement call. Understanding the selection criteria in advance helps set realistic expectations. It also reduces the chance of disappointment once treatment begins.
What Knee Osteoarthritis Stage Suits an Arthrosamid Candidate
Disease severity is the single biggest factor in candidate selection. Clinicians grade knee osteoarthritis using the Kellgren-Lawrence grade. This scale runs from 0 to 4. It reflects how far cartilage loss and bone changes have progressed. Most successful arthrosamid candidates sit at grade II or III. This means moderate cartilage loss without complete joint space collapse.
The grading scale breaks down broadly as follows:
- Grade 0 or 1: no clear disease, or minimal changes with little clinical relevance
- Grade 2: definite narrowing with early bone spur formation, often mild symptoms
- Grade 3: moderate narrowing with multiple bone spurs and some joint deformity
- Grade 4: severe narrowing with bone-on-bone contact and marked deformity
Patients with early, mild symptoms rarely need Arthrosamid at all. Conservative measures usually manage grade 1 disease adequately on their own. At the opposite end, grade 4 changes usually predict a poor injection response. The chance of eventually needing surgery is also higher at this stage. Clinicians stay cautious with patients sitting right at this boundary. Expectations need managing carefully whichever way the assessment concludes. A borderline grade 3 to 4 knee may still respond to treatment. The improvement is often smaller and shorter-lived than in a clearer grade 2 or 3 case. An MRI scan is occasionally requested alongside an X-ray for unclear cases. This gives a fuller picture of cartilage thickness and any hidden joint damage.
A large UK cohort study followed 269 patients across 314 knees for 24 months. It found that lower disease grade was independently linked to better outcomes. Older age and absence of diabetes were linked to better outcomes too. A radiologist or specialist clinician usually confirms the grade from imaging. This is precisely why disease staging happens before any decision on treatment proceeds. Pain intensity alone does not always match the true extent of joint damage. The distinction between early and advanced disease shapes broader orthopaedic strategy as well. Non-surgical orthopaedic treatment changes considerably between early and advanced joint damage, not just injection choice.
Core Criteria for Arthrosamid Eligibility

Beyond imaging grade, several patient-level factors influence arthrosamid eligibility. Clinicians weigh these together rather than relying on any single measure. No individual test fully predicts who will respond well to treatment.
Age, Diabetes Status and Bilateral Involvement
Research consistently links three additional factors to stronger outcomes:
- Older age
- Absence of diabetes
- Bilateral knee involvement
Patients without diabetes tend to respond more consistently to the hydrogel injection. Diabetes may be linked to broader changes in joint tissue healing. Bilateral symptoms, somewhat counterintuitively, also predicted better results in cohort data. This possibly reflects a more diffuse but earlier-stage disease pattern. A single severely damaged joint bearing all the load behaves differently.
Age plays a role, but not as a simple exclusion:
- Age itself is not an exclusion criterion in either direction
- Older patients often present with more established, stable disease patterns
- These patterns tend to respond predictably to treatment over time
- Younger patients are not automatically excluded from consideration either
- Clinicians look more closely at activity level and treatment goals in younger cases
- A younger, highly active patient may place different demands on the joint
None of these factors works as a strict cut-off in isolation. A younger patient with well-controlled diabetes may still qualify. This depends on full clinical review of the whole case. Arthrosamid patient selection always accounts for the whole clinical picture. No single data point is considered on its own. This is exactly why a formal consultation matters more than any single test.
Body weight is another factor clinicians often review during assessment:
- Extra weight increases mechanical load through the knee joint
- Carrying less weight can reduce symptoms and support the benefit gained from treatment
- Weight does not usually exclude a patient outright from candidacy
- Weight often forms part of the wider treatment discussion instead
Failed Conservative Treatment as a Prerequisite
Most clinics require evidence that conservative treatment has already been tried. This typically includes structured physiotherapy and weight management advice. Oral analgesics used consistently over several months also count. Persistent pain despite these measures strengthens the case for injection therapy.
This step exists for a clear reason. It avoids offering an interventional option before simpler measures have had a fair trial. It also protects patients from unnecessary procedures. Symptoms might still improve naturally with lifestyle changes or gradual weight loss. A revised, targeted exercise programme can also help before injections are considered.
Who Should Avoid Arthrosamid Injection

Certain conditions rule out Arthrosamid regardless of osteoarthritis grade. This applies even with an otherwise favourable patient profile. Active joint infection is an absolute contraindication. Introducing implant material into an infected joint carries a serious risk. Infection could spread deeper into surrounding tissue as a result. Patients who previously received a different non-absorbable implant are also excluded. Combining materials of this kind is not supported by current safety data.
Additional exclusions typically include:
- Recent knee arthroscopy, usually within the past six months
- Uncontrolled bleeding disorders or ongoing anticoagulant treatment
- Known allergy to polyacrylamide or other gel components
- Presence of a knee replacement or other foreign material already in the joint
- Active skin infection or broken skin near the planned injection site
- Pregnancy or breastfeeding, and patients under the age of 18
Arthrosamid is currently licensed for knee osteoarthritis only. It is not approved for use in other joints such as the hip or shoulder. Patients previously given a degradable injection normally need a waiting period. Six weeks is standard after a corticosteroid injection. Three months is standard after hyaluronic acid or PRP. This allows the earlier product to clear fully from the joint space. Skipping this washout period risks an unpredictable reaction inside the joint capsule. These arthrosamid contraindications are consistent across UK specialist centres. They form a core part of every screening consultation before treatment is confirmed.
Arthrosamid vs Other Knee Injections
Understanding how Arthrosamid differs from established alternatives clarifies why selection matters. The same patient might suit one injection option but not another entirely.
Arthrosamid vs Hyaluronic Acid Injection Knee
A hyaluronic acid injection knee treatment temporarily supplements joint fluid. It is gradually absorbed by the body over weeks to months. Arthrosamid, by contrast, is designed to remain in place indefinitely. It works as a mechanical cushion rather than being broken down naturally. A retrospective cohort compared both approaches directly over twelve months. Pain scores in the hyaluronic acid group had returned close to baseline. The Arthrosamid group retained modest but measurable improvement over the same period. This durability gap is the main clinical reason patients switch between the two. Many move from repeated hyaluronic acid courses to a single Arthrosamid treatment.
Arthrosamid vs Corticosteroid Injection Knee
A corticosteroid injection knee treatment works quickly to dampen inflammation. It rarely lasts beyond a few weeks or months before symptoms return. Arthrosamid takes longer to reach peak effect, generally three to twelve months. The benefit, however, tends to persist for years rather than weeks. Neither option regenerates cartilage in the joint. Both remain reasonable choices depending on how quickly relief is needed. Cost is another factor patients weigh during this decision. Arthrosamid cost in the UK reflects a single procedure rather than repeated courses. Some patients whose earlier gel injections for knee pain stopped working move toward Arthrosamid. This pattern is explored further in gel injections for knee pain as a non-surgical option. PRP is a third alternative some patients try before considering Arthrosamid. Evidence directly comparing PRP with Arthrosamid remains limited at present.
The Arthrosamid Patient Selection and Assessment Process
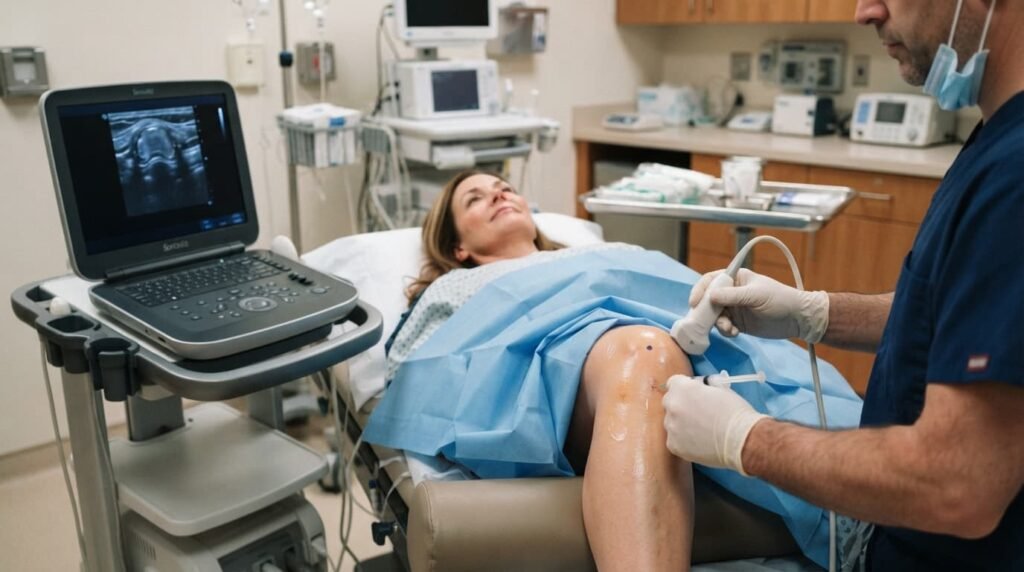
Formal assessment steps typically begin with a specialist consultation. This first appointment usually lasts around 30 to 45 minutes. The consultation reviews symptom history, previous treatments, and daily activity limits. Patients are welcome to seek a second opinion before committing to any procedure. Recent knee osteoarthritis imaging is usually required within the past twelve months. An X-ray confirms the disease grade and rules out advanced bone-on-bone change.
A typical assessment pathway includes:
- Initial consultation covering symptom history and prior treatments
- Physical examination of knee range of movement and stability
- Recent imaging review, or arranging new imaging if none exists already
- Discussion of realistic expected outcomes and available treatment alternatives
- Formal confirmation of eligibility before booking the procedure date itself
- Discussion of alternative treatment routes if Arthrosamid is not appropriate
If imaging and history support candidacy, treatment can then be booked. The injection itself is delivered under an ultrasound-guided knee injection technique. This lets the clinician confirm accurate needle placement within the joint capsule. Placement is confirmed before the full dose is released into the joint. This reduces the chance of missed placement compared with older landmark-only methods. Ultrasound guidance also lets the clinician check for residual fluid or inflammation. Patients are asked about realistic expectations during this stage as well. Arthrosamid is a cushioning treatment rather than a cure. Understanding that distinction upfront improves satisfaction with the eventual outcome.
What Happens After Confirmed Candidacy
Arthrosamid is delivered as a single injection rather than a repeated course. Mild soreness and swelling in the first 48 hours are entirely normal. This is a tissue response rather than a sign of complication. Arthrosamid recovery generally allows walking immediately after the procedure. Driving is usually delayed for 24 to 48 hours as a precaution. Most patients return to light daily activity within a day or two. Heavier exercise, running and gym sessions are usually paused for one to two weeks.
Simple aftercare steps during the first few days include:
- Applying a wrapped ice pack for short periods to reduce swelling
- Keeping the leg elevated when resting at home
- Using paracetamol for mild discomfort following standard dosing guidance
- Avoiding baths, swimming or soaking the injection site until fully healed
Regarding arthrosamid side effects, most issues are limited to temporary local swelling. Bruising or stiffness is common and settles without specific treatment. Serious complications, particularly infection, remain uncommon after the procedure. Urgent review is needed if fever or worsening redness develops afterwards. Severe, escalating pain in the days following treatment also needs urgent review. Once the initial recovery window passes, a structured strengthening programme often helps. Stronger muscles around the knee reduce the mechanical load the joint carries. A follow-up review appointment is often scheduled around the six to eight week mark.
Long-term data support the durability that makes Arthrosamid attractive for suitable candidates. A five-year open-label extension recorded a mean WOMAC pain score improvement of 14.6 points. A separate randomised trial extension reported a 16.2-point improvement at the same time point. Both figures represent Arthrosamid 5-year results well above a clinically meaningful threshold. A systematic review pooling 463 patients noted a further encouraging finding. Arthrosamid achieved among the highest patient-acceptable symptom state rates of any injection type. This is exactly why correct candidate selection at the outset matters so much. It shapes long-term satisfaction more than almost any other factor. Further explanation of non-surgical knee osteoarthritis management appears in a video on the Dr SNA Clinic YouTube channel.
When Advanced Arthritis Rules Out Arthrosamid
Patients with grade 4, bone-on-bone disease are the clearest exception to candidacy. This applies regardless of age or other otherwise favourable factors. In cohort data, higher osteoarthritis grade was the strongest predictor of one outcome. That outcome is eventually needing total knee replacement surgery. Roughly 18% of one large cohort reached surgery within two years. Knee injections fail in advanced arthritis for several clear reasons. No injectable material can restore meaningful cushioning once cartilage space is gone entirely.
For these patients, discussion typically shifts toward knee replacement surgery UK pathways. Realistic waiting time expectations replace further injection attempts unlikely to help. Recognising this distinction early avoids delayed referral and repeated failed procedures. It also helps patients plan realistically around surgery timelines instead. Data consistently show injections perform poorly at this advanced disease stage. Referral to an orthopaedic surgeon becomes the more useful next step in that scenario.

Frequently Asked Questions
What makes someone a good arthrosamid candidate?
Mild-to-moderate knee osteoarthritis, confirmed by imaging, is the starting point. Persistent symptoms despite conservative treatment also matter. Older age, absence of diabetes and bilateral involvement are linked to stronger outcomes.
Is arthrosamid patient selection based on age alone?
No single factor decides eligibility on its own. Age is considered alongside disease grade and general health. Response to prior conservative treatment also plays a part in the final decision. Overall general health and fitness for a minor outpatient procedure are reviewed too.
How does arthrosamid vs hyaluronic acid compare for older patients?
Hyaluronic acid gives shorter-term relief through temporary joint lubrication. It is gradually absorbed and needs repeating over time. Arthrosamid tends to offer more durable benefit for suitable candidates.
Does Arthrosamid suit patients heading toward total knee replacement?
Generally not. Advanced, bone-on-bone disease responds poorly to Arthrosamid injection. Surgical pathways become the more appropriate discussion at that stage.
How long does the arthrosamid assessment process usually take?
Most patients complete consultation and eligibility confirmation within a single appointment. Additional imaging is arranged separately if recent scans are not already available.
Is Arthrosamid suitable for every joint affected by osteoarthritis?
No. Arthrosamid currently carries a licence for the knee joint only. Other joints, such as the hip, are not covered by current approval.
Arthrosamid candidate selection depends on osteoarthritis stage and treatment history together. Specific health factors matter too, rather than age alone. Mr Syed Nadeem Abbas provides an individual assessment to confirm suitability first. This uses an imaging review and a full medical history before any treatment proceeds.
Read more: Top Mistakes After Knee Replacement Often Go Unnoticed Until Too Late
Read more: Cysts Behind the Knee Can Signal Several Different Joint Conditions